4 September 2026

First-in-Human vs. First-in-Patient: How to Choose

First-in-Human vs. First-in-Patient: How to Choose

First-in-Human vs. First-in-Patient: Which Should You Start With, and Why It Matters for Your Timeline

Deciding who gets the first dose of your investigational product is one of the earliest, highest-stakes calls in a drug development program. Get it right, and you set up a clean data package that supports your next investor conversation and your next regulatory milestone. Get it wrong, and you may be looking at unplanned work that eats into the tightest part of your timeline: protocol amendments, bridging studies, or maybe even a total redesign.

For teams building a global program, that decision doesn’t stand alone. Where you run the study can amplify, or offset, the advantage of getting the population choice right.

FIRST-IN-HUMAN STUDIES VS. FIRST-IN-PATIENT STUDIES: WHAT’S THE DIFFERENCE?

A first-in-human (FIH) study is the first time an investigational product (the drug) enters a human body, and that body belongs to a healthy volunteer. The goal is to understand safety, tolerability, and pharmacokinetics (PK), which describes how the body absorbs, distributes, and clears a drug, in a “clean” population, before it’s known whether the drug provides any therapeutic benefit.

A first-in-patient (FIP) study is when the first dose enters the body of a patient who has the disease you’re targeting. This happens either because it would be unethical to expose a healthy person to the drug’s risk profile, or because the drug’s pharmacological target only exists in someone with the disease.

The choice determines almost everything that follows:

  • Who your eligible population is
  • What kind of sites and investigators you need
  • How you monitor safety
  • Your participant recruitment strategy
  • How quickly you might generate a signal that supports your next investor conversation.

HOW TO DECIDE WHICH STUDY DESIGN FITS YOUR PROGRAM

The decision comes down to a few concrete questions about your molecule, your indication, and your risk profile — and in many cases, an approach that blends the two rather than choosing one.

Questions to Ask Before the Protocol Gets Written

Start with the mechanism itself. A few questions worth asking early that can save later-stage rework:

  • Does the drug’s risk profile make dosing a healthy volunteer ethically or scientifically indefensible?
  • What does regulatory precedent look like for this drug class? Has a regulatory agency already signaled an expectation for one approach over another?
  • Will starting in patients actually shorten your path to proof-of-concept, or will it add complexity you haven’t budgeted for?
  • Is there enough of a preclinical safety margin (the gap between an effective dose and a harmful one) to justify healthy volunteer exposure at all?

Hybrid Designs: Not Always Either/Or

This isn’t always a strict either/or decision. Many programs blend both populations within a single Early Phase study. A common pattern is running single ascending dose (SAD) and multiple ascending dose (MAD) cohorts in healthy volunteers to establish a safety baseline, then opening expansion cohorts in patients under the same adaptive or umbrella protocol once there’s enough safety data to justify it.

The advantage of a hybrid approach is that it lets a sponsor understand the fundamental safety, tolerability, and PK profile of the drug, while also capturing an early efficacy or pharmacodynamic signal. That information is critical for licensing conversations and de-risks go/no-go decisions.

when a first-in-human study makes sense

Traditional FIH still makes the most sense for programs where the predicted safety margin is favorable (low risk). This typically includes therapeutic areas such as metabolic, cardiovascular, respiratory, or dermatology conditions, where a healthy person’s physiology is reasonably representative of the eventual patient population.

Starting there gets you cleaner data, for a few reasons:

  • Healthy volunteers aren’t taking concomitant medications for other conditions
  • They don’t have comorbidities that confound results
  • The volunteer pool is larger and faster to recruit from than most patient populations

That combination of speed and data clarity is exactly why the traditional model has stayed the default for so long. It’s the most efficient way to determine whether the drug is safe, how it behaves in the human body, and how the body metabolizes it, before disease adds its own variables into the mix.

when a first-in-PATIENT study makes more sense

Oncology is the most familiar example of a patient-first default, but it isn’t the only one.

CNS Programs

Central nervous system (CNS) programs in which behavioral and psychiatric effects are unpredictable are a good example for a couple of reasons. Typically, these CNS-active compounds cross the blood-brain barrier and produce neurological or psychiatric effects that are too unpredictable and too hard to justify in someone who doesn’t have the condition. On top of that, many of the pharmacodynamic markers used to indicate efficacy (disease-specific EEG patterns, cognitive or seizure activity, for example) don’t exist to be measured in a healthy person. Avance Clinical’s CNS and neuroscience team works through these design questions with sponsors regularly.

Ophthalmology Programs

Ophthalmology is another one, and it’s less about the drug itself and more about how it has to be delivered. Many ophthalmic therapies, especially anti-VEGF biologics and retinal gene therapies, are administered by intravitreal or subretinal injection. Regardless of how safe that drug is, the route of administration carries inherent risk, such as retinal detachment or infection inside the eye. Exposing a healthy eye to that procedural risk can’t be justified. Gene therapies for inherited retinal disease add another layer, since the genetic mutation they target (and the resulting benefit) only exists in someone who actually has the disease.

That said, not every ophthalmology study fits this pattern. Therapies delivered as eye drops for conditions like glaucoma or dry eye disease are far less invasive, so corresponding studies can start in healthy volunteers.

Rare Disease, Cell and Gene Therapy, and Immunology Programs

For rare disease and gene or cell therapy programs, the biological target is often only present in the disease state. This means the eligible patient population is already small, and in many cases the intervention is irreversible, which raises the ethical bar for justifying any use in someone without the disease. Severe autoimmune and immunology programs with strong immunosuppressive potential follow the same logic: the risk of infection to a healthy volunteer can outweigh any information the study would reveal.

THE RISK OF CHOOSING THE WRONG STUDY DESIGN

Getting this decision wrong rarely shows up as one big failure. It tends to surface as a series of smaller problems that add up, in your timeline, your budget, and your key relationships.

Timeline and Cost Impacts

If the study design doesn’t align with your program’s timeline, regulatory pathway, or resources, you’re looking at a slow accumulation of course corrections. For example, if the eligibility criteria were too narrow or too broad for the population you actually needed, you might need to amend the protocol as the study is running, which also means going back through ethics or regulatory review, and that costs time and money. You might also discover that healthy volunteer PK doesn’t translate cleanly to your patient population, meaning the FIH data doesn’t actually support dose selection for the next study, so an additional PK bridging study is needed.

In more serious cases, a regulator may push back if the ethical justification for your chosen population doesn’t hold up, which can mean a clinical hold or a redesign, adding even more time to your development pathway. All of this compounds because early-phase timelines are usually the tightest part of a program’s runway.

Less Quantifiable Costs

Repeated protocol amendments can create real friction with investigators and site staff, often slowing down momentum and site engagement. Those relationships are something your team will draw on again and again across the development timeline, so friction there can have a long-lasting impact.

On the investor side, a program that has to pause, amend, or redesign its early-phase study plan altogether raises governance questions that are likely to get scrutinized ahead of the next fundraising event. And internally, the more a study team pivots the strategy, the more likely they are to lose institutional knowledge and momentum, which can delay the entire program.


WHY GLOBAL STUDY PLACEMENT AFFECTS YOUR PROGRAM TIMELINE

Population design is one lever on your timeline. Where you run the study is another, and the two decisions don’t exist in isolation. The best region is the one where the study can be executed the fastest, most cost-effective way, and where the resulting data will be accepted widely by regulators. Regulatory pathways vary widely in how much upfront documentation they require, how long ethics and regulatory review takes, and whether they demand a full investigational new drug (IND) style dossier before dosing can commence.

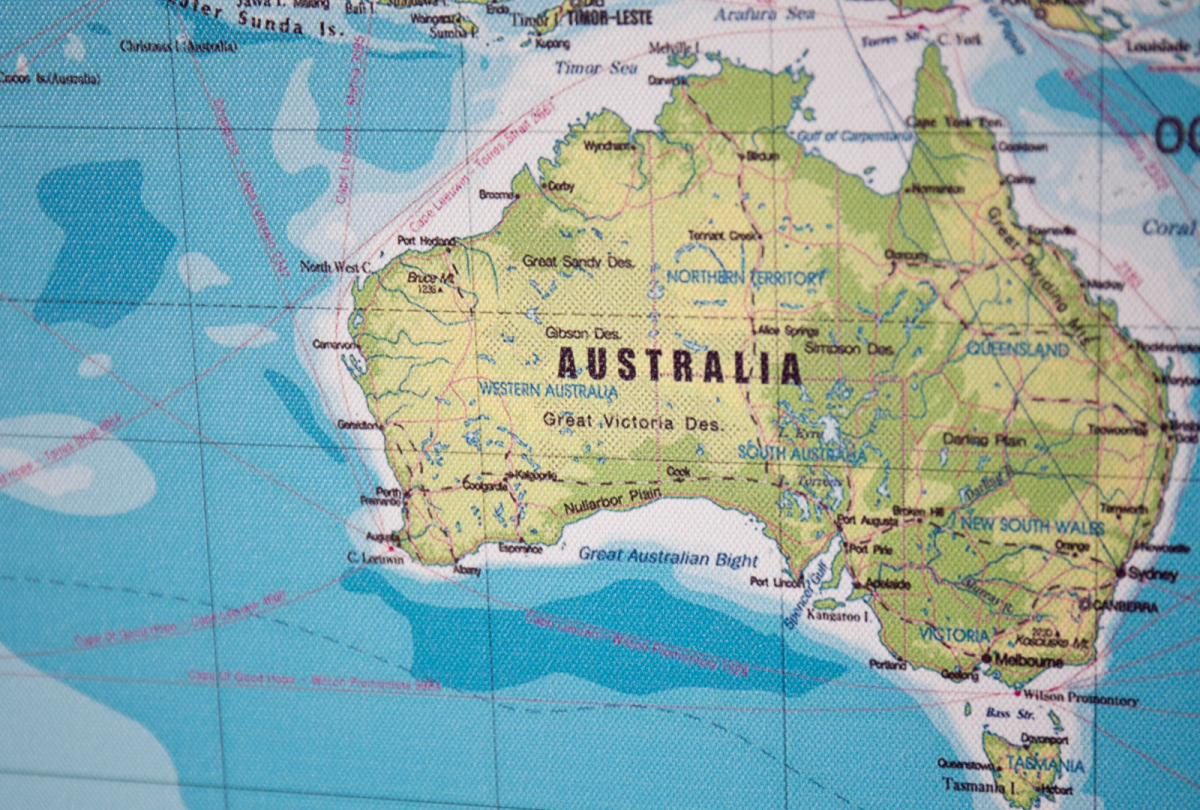
Australia is a useful example here, not because it’s the only option, but because it illustrates the kind of trade-off sponsors should be evaluating everywhere. Under the Therapeutic Goods Administration’s (TGA) Clinical Trial Notification scheme, ethics committee approval is the substantive review, and the regulator is simply notified rather than conducting its own upfront assessment. That can mean starting a study in a matter of weeks rather than months, without an IND-equivalent submission. Data generated in Australia is also accepted (subject to GCP compliance) by agencies including the FDA, EMA, and PMDA, so sponsors aren’t sacrificing global readiness for speed.

You should also evaluate factors like:

  • Population availability in a given region for the specific indication
  • How a regional data package will be viewed when it’s time to support a multi-regional pivotal trial
  • Seasonal considerations, where applicable
  • The practical realities of site activation timelines and cost

If you’re weighing where and how to run your first clinical trial, talk to an expert at Avance Clinical to determine which route best fits your molecule, your indication, and your timeline, wherever in the world you’re building.

About the Author

Jemma Lawson

Jemma Lawson

Executive Vice President, Global Operations

Jemma Lawson's LinkedIn Profile

Read more

Related Items